
Clinical Obesity: The New Definition Beyond BMI
Clinical obesity is a new way to diagnose obesity beyond BMI. See what a study of 844,108 adults found and how to check your own waist and BMI numbers.
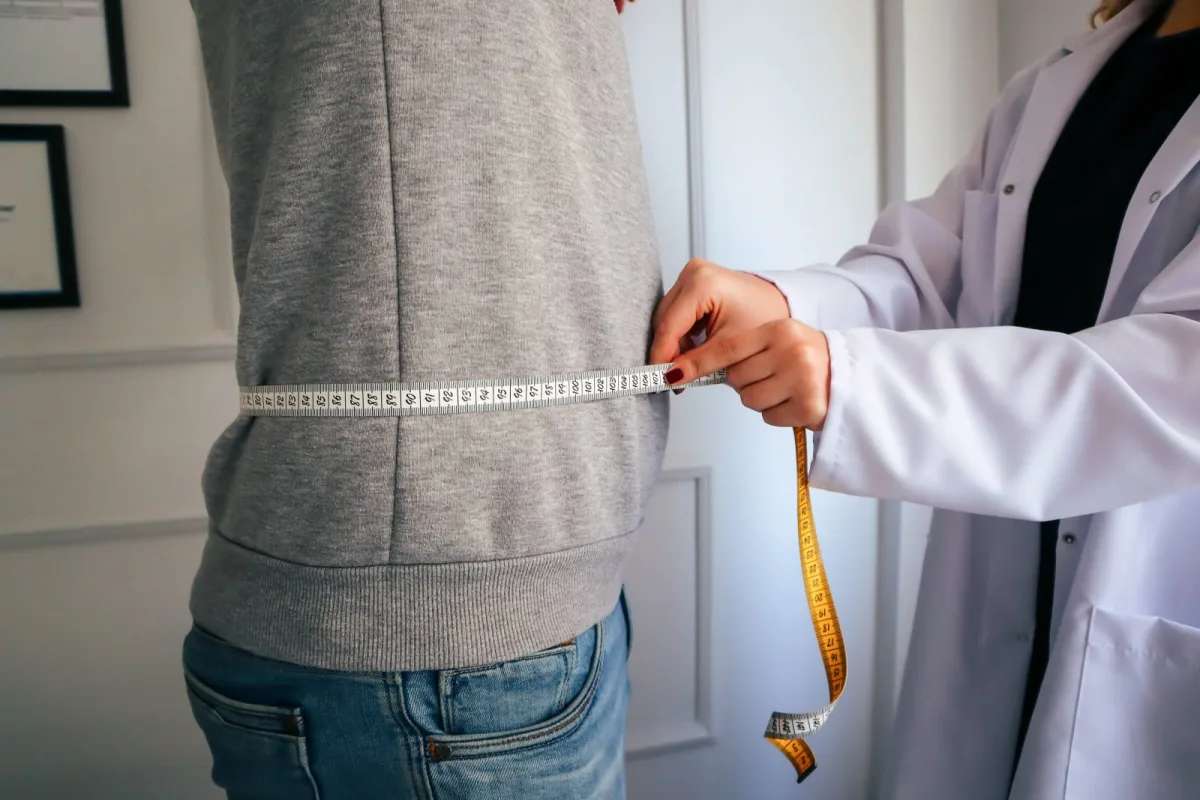
Table of contents
You step on the scale at your checkup, the nurse does the math, and your BMI comes back at 31. The chart says obese. Your friend, who never lifts weights and carries most of his weight around his middle, sits at 27 and gets told he is merely overweight. You both leave wondering whether the number means anything.
A major study published in Nature in November suggests your doubts are fair. It tested a new way to diagnose clinical obesity, one that adds waist measurements to BMI and then asks a second question: is excess fat already harming your body? The answer changed the diagnosis for millions of people. Here is how the new definition works, what the study found, and how to run your own numbers before your next appointment.
Why BMI Gets So Many People Wrong
Body mass index is your weight in kilograms divided by your height in meters squared. The World Health Organization classes a BMI of 25 or more as overweight and 30 or more as obese. It is cheap, fast, and needs nothing but a scale and a tape.
It is also blunt. BMI cannot tell muscle from fat, and it cannot see where fat sits. Fat packed around your organs behaves differently from fat on your hips, yet BMI treats every kilogram the same. A muscular person can score as obese, and someone with a large waist and thin limbs can slip under the line.
The stakes are large. The WHO estimates that 1.1 billion people worldwide, about 1 in 7, were living with obesity in 2024. Adult obesity has more than doubled since 1990. When a label covers that many people, a small error rate still adds up to millions of wrong diagnoses in both directions.
The Clinical Obesity Framework, Explained
Last year, a commission published in The Lancet Diabetes and Endocrinology proposed a two-step approach. Its goal was to separate people whose weight is harming them right now from people who simply carry extra risk.
Step one: confirm the excess fat
Instead of relying on BMI alone, the framework pairs it with a body measure. Under the criteria used in the Nature study:
- BMI of 40 or more counts on its own.
- BMI of 30 to 39.9 needs either a large waist or a high waist-to-height ratio.
- BMI of 25 to 29.9 needs both a large waist and a high waist-to-height ratio.
A large waist means at least 102 centimeters (about 40 inches) for men and 88 centimeters (about 35 inches) for women, with lower cutoffs and lower BMI bands for Chinese adults. Waist-to-height ratio thresholds ranged from 0.50 to about 0.59 depending on ethnicity.
Step two: check what the fat is doing
Once excess fat is confirmed, the question becomes function. Clinical obesity means excess fat that is already impairing organs or daily life. Preclinical obesity means more fat and higher risk, but organs and whole-body function are still working normally.
The commission set out 18 diagnostic criteria for adults. Meeting any one of them moves you into the clinical group. Examples include:
- Heart failure, atrial fibrillation, or high blood pressure
- Obstructive sleep apnea
- Fatty liver disease with scarring
- Chronic kidney disease
- Hip or knee osteoarthritis
- Combined high blood sugar and abnormal blood fats
- Limits on everyday activities caused by excess weight
That last item matters. You do not need a lab result to qualify. If excess weight stops you from doing ordinary things, the framework treats that as illness.
What the New Clinical Obesity Study Found
An international team of researchers tested the framework on real records from four large cohorts: the Kailuan Study in China, the UK Biobank, the US All of Us Research Program, and Spain's SIDIAP primary care database. Together they covered 844,108 adults.
Three findings stand out.
- More people had obesity, not fewer. The combined definition raised prevalence by 3.3 to 7.4 percentage points. In the UK Biobank it went from 24.0% to 27.3%. In the US cohort it rose from 42.5% to 48.1%.
- Only a minority had clinical obesity. Between 22.7% and 31.3% of people with obesity met a clinical criterion. In the US cohort, 10.9% of all adults had clinical obesity.
- The split tracked survival. Clinical obesity carried a hazard ratio of 1.69 for death from any cause. Preclinical obesity carried 1.19. People flagged by BMI alone, but not by the new criteria, showed no higher risk; their pooled estimates were slightly below 1.
The link between clinical obesity and death was stronger in women and in people under 60. STAT, which covered the paper, noted that the split could make diagnosis more precise while raising new questions about who should be treated.
The limits
The authors are candid about the weak points. Organ problems were found through billing and medical record codes rather than standardized exams. Not every cohort could check all 18 criteria; one could measure only nine. The design looked backward at existing records, so the authors call for prospective studies with confirmed diagnoses. Some obesity groups, including the Obesity Medicine Association and the European Association for the Study of Obesity, have also criticized parts of the framework.
A Worked Example: Three People, Same Height
Take three men, each 175 centimeters tall (about 5 feet 9 inches). Their height squared is 3.06, so BMI is weight divided by 3.06.
Man A weighs 95 kg and has a 106 cm waist. His BMI is 31.0, so BMI calls him obese. His waist is over 102 cm, which confirms excess fat under the new rules. He has obesity on both systems.
Man B weighs 82 kg and has a 104 cm waist. His BMI is 26.8, so BMI calls him overweight. But his waist is over 102 cm, and his waist-to-height ratio is 104 divided by 175, or 0.59. That clears even the highest threshold in the study. With both measures high, the new framework says Man B has obesity that BMI missed.
Man C is a weightlifter at 98 kg with an 84 cm waist. His BMI is 32.0, firmly obese on the chart. His waist is normal and his ratio is 0.48, below every threshold. Because his BMI is under 40, the new framework does not confirm obesity at all.
Now apply step two. If Man A has knee osteoarthritis or sleep apnea, he has clinical obesity. If his organs and daily life are unaffected, he has preclinical obesity. Man B goes through the same check. One extra tape measurement just flipped two of three diagnoses.
What This Means for You and Your Doctor
The framework has not replaced BMI in everyday practice, and your clinic may not use it yet. You can still bring its logic to your next visit.
- Ask for a waist measurement. It takes seconds and adds information BMI cannot give. If you track it at home, measure at the same spot and time of day each time so the numbers are comparable.
- Name any limits on daily life. Joint pain on stairs, breathlessness, or trouble with routine tasks are part of the diagnosis, so say them out loud.
- Ask which conditions to check for. Blood pressure, blood sugar, liver tests, and a sleep apnea screen map onto the clinical criteria.
Diagnosis shapes treatment. Clinical obesity is framed as an active illness, which may strengthen the case for medical treatment, including the newer weight-loss drugs. If you are weighing those, our breakdown of what GLP-1 drugs actually cost each month covers the money side. Since combined blood sugar problems are one of the criteria, it also helps to know why undiagnosed diabetes rarely causes symptoms.
For preclinical obesity, the study offers some reassurance: most people in that group stayed there for a decade. That leaves room to cut risk with habits you control, and building muscle is one of the best documented. Our look at strength training and longevity explains how much is enough. Talk to your clinician before starting any new treatment or major change in diet or exercise.
Frequently Asked Questions
What is the difference between clinical and preclinical obesity?
Both involve confirmed excess body fat. Clinical obesity means that fat is already impairing organs or daily activities, through problems such as heart failure, sleep apnea, or knee osteoarthritis. Preclinical obesity means higher future risk with normal function for now.
Is BMI still used to diagnose obesity?
Yes. The WHO still defines adult obesity as a BMI of 30 or more, and most clinics rely on it. The newer framework keeps BMI as a starting point but adds waist measures and a check for organ or functional problems.
What waist size counts as obesity?
In the criteria used in the Nature study, a waist of at least 102 cm (about 40 inches) for men or 88 cm (about 35 inches) for women counts as elevated, with lower cutoffs for Chinese adults. It confirms obesity only alongside a qualifying BMI.
Can you have obesity with a BMI under 30?
Under the new framework, yes. A BMI between 25 and 29.9 qualifies if both your waist size and your waist-to-height ratio are elevated. The study found BMI alone missed obesity in 5.2% to 8.6% of people.
The Bottom Line on Clinical Obesity
BMI was built to describe populations, and it shows. The clinical obesity framework asks two better questions: is there truly excess fat, and is it already doing harm? In 844,108 people, those questions sorted risk far more sharply than BMI did, even if the tools to apply them still need refining.
You do not need to wait for your clinic to adopt it. Know your waist size, know your BMI, and be honest about what your body can and cannot do day to day. Those three facts give you and your clinician a much clearer picture than a single number on a chart.
Written by
Priya Raman
Health & Living
Covers health, wellness, and everyday living for Quick Trend Insights, with an interest in separating what the research supports from what the marketing claims.
Related Articles
View all
Daraxonrasib Pancreatic Cancer Trial: What It Found
Daraxonrasib pancreatic cancer trial explained: what the phase 3 study found on survival and side effects, why RAS was undruggable, and who can get it now.
CTE Blood Test: What the New Studies Actually Show
A CTE blood test may one day diagnose the disease in living people. What two new JAMA studies found, their accuracy limits, and who the test could matter for.
Coronary Calcium Score: Do You Need a CAC Test?
A coronary calcium score can settle whether you need a statin. See what the CorCal trial found, what the scan costs, and who should skip the CAC test.